

Choosing a medical specialty with a spouse works best when both partners rank training length, call, income and location against shared family goals before comparing individual specialties.
Picture the usual standoff. One partner is drawn to a specialty they find fascinating, while the other is counting the years of training and the nights on call. Both concerns are legitimate, and neither settles the question alone.
- Agree on limits first. Decide what the household cannot bend on: region, schedule predictability and how long training may last.
- Then compare specialties. Test each one against those limits using program-level answers, not reputation.
- Keep clinical fit with the physician. The partner who will do the work has the final say on what work holds their interest.
Readers who are married to a doctor will find the wider relationship context for these decisions in the Physician Marriages guide. The steps below break the choice into the problems couples most often get stuck on.
Weighing a spouse’s input
A spouse’s input should carry real weight on the parts of a specialty the whole household lives with, and less on clinical fit that only the physician experiences. ACOFP residency guidance says the ideal family medicine residency aligns with personal preferences and priorities. For a married couple, those priorities are shared ones.
Shared ground and personal fit
- Weighted toward the household: where you will live, how predictable the schedule is, and how long the family plans around a trainee’s hours.
- Weighted toward the physician: the type of clinical work, the patients, and whether the daily routine is something they can sustain with enthusiasm.
- Weighted equally: anything that changes the next several years of home life, such as a second move or an extra year of training.
A ranked-priorities exercise
A written exercise keeps the conversation from becoming a contest of who feels more strongly.
- Write separate lists of non-negotiables, without consulting each other.
- Merge the lists and mark every item that appears on both.
- Rank the merged items from most to least movable.
- Score each specialty under consideration against the top of that ranking.
Training length and fellowship
Residency length is the first hard comparison, because it sets how long the household plans around a trainee’s schedule. Family medicine offers a worked example. ACOFP describes 3 years of supervised training as the foundation of the specialty, and a peer-reviewed analysis of the field reports endorsement of lengthening family medicine residency to 3 years.
Even a defined residency does not always mark the end of training. It also reports that optional third-year training grew from 85 trainees in 1996 to 1997 to 242 in 2010 to 2011. The point for couples is that the nominal length of a specialty is a starting figure, and extra years are often added by choice.
Fellowship as a second decision
A fellowship is a separate decision after residency, and it extends the training horizon. ACOFP notes that while the majority of family medicine physicians opt for primary care roles after residency, some pursue fellowships. Couples should discuss whether the physician is likely to want one before committing to a specialty, because a fellowship can bring another application cycle and possibly another move.
For any other specialty, take the length and structure from that specialty’s ACGME program requirements, and count each fellowship year as part of the same planning horizon. The guide to marriage during residency is a useful companion for thinking about what those years mean at home.
Couples with a firm timeline for starting a family or settling in one place should weigh a shorter, defined path more heavily. Couples with more flexibility can reasonably accept longer training for a specialty the physician cares about deeply.
Call and weekly rhythm
Call is something to ask about, not assume, because it differs between programs as well as between specialties. ACOFP advises that students should inquire about resident wellness initiatives, feedback mechanisms, didactics and on-call schedules. A spouse can add to that list the questions that matter at home: how call is distributed, how coverage works when a resident is ill, and how far in advance schedules are released.
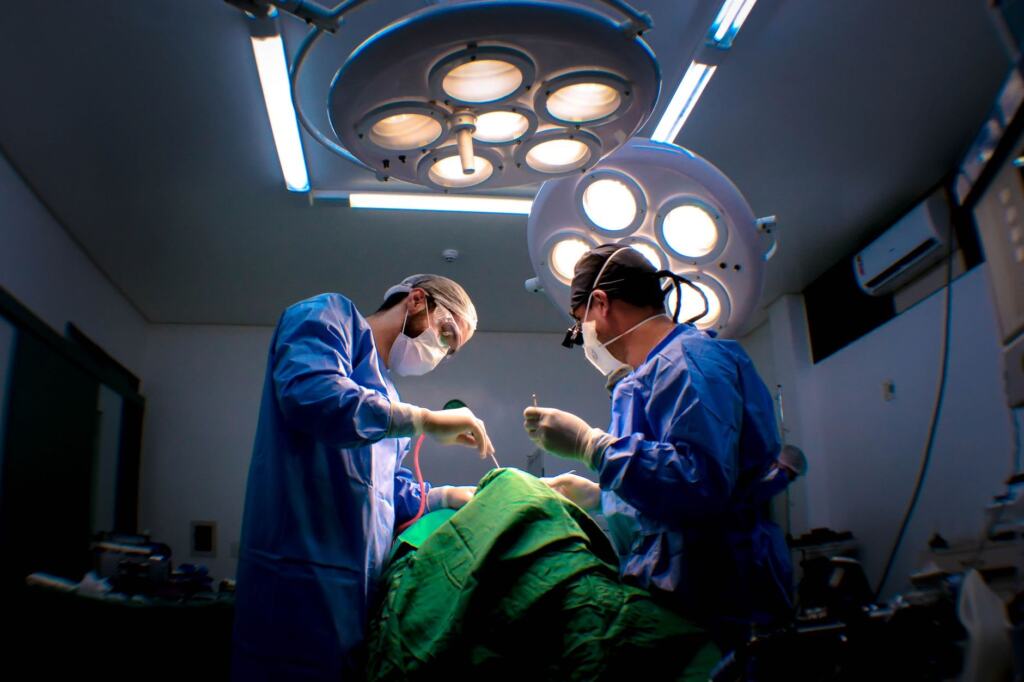
Procedural specialties build the week around operating schedules and the demands of cases, so the questions should cover how cases and call combine for residents.
A clinic-based specialty deserves the same questions, since outpatient work and call can coexist. Do not treat a clinic setting as a guarantee of regular hours. Ask the program and, where possible, current residents and their partners.
Income and lifestyle trade-offs
Income and lifestyle should be treated as a trade the couple makes deliberately, not a ranking to copy from a list. Published physician compensation reports are a reasonable input. Read them alongside the training length and call questions above, because a pay figure means different things at different workloads.
- If a financial target drives the plan: look at how long the household will wait before the physician reaches full practice, and whether a fellowship is likely to be part of the route.
- If time at home drives the plan: prioritise program-level answers on call and schedule over any specialty-wide reputation, and accept that this may narrow the options.
- If both matter: decide in advance which one gives way when they conflict, so the decision is not made under pressure at ranking time.
A couple that names the trade openly usually decides faster than one that hopes the numbers will make the choice for them.
Where you can live
Specialty choice affects where a couple can live because training takes place at particular programs in particular places. ACOFP reports that 773 family medicine categorical and combined residency programs participated in the 2023 match. A specialty with many programs gives a couple more locations to screen, while a specialty with few programs narrows the map before preferences even enter.

Setting and quality of life
The same ACOFP guidance notes that urban settings often yield higher patient volumes, which means more exposure, than rural ones. It also lists proximity to family and friends, local crime rates and recreation among the quality-of-life considerations for residents. For a couple, the practical reading is to decide early whether being near relatives or a spouse’s job outweighs a program’s training volume.

Plan a fallback as well. Partners who want a contingency can read through didn’t match residency what now marriage before ranking programs, since it is easier to discuss options calmly before results than after.
Troubleshooting a stalemate
- One partner calls the other’s concern minor. Ask for the specific scenario behind it, such as a holiday spent on call, and bring that scenario to programs as a question.
- The preferred specialty has no program in an acceptable region. Decide whether geography or specialty gives way. If neither will, explore related specialties that share the clinical work the physician values.
- The information is secondhand. Replace stereotypes about a specialty with answers from programs and current residents.
- The conversation keeps looping. Ask a mentor who knows both the specialty and your situation to review your ranked priorities and point out what is missing.
Frequently asked questions
| Question | Answer |
|---|---|
| Does SF Match follow the same timeline as the NRMP match? | No. A residency match guide states that SF Match operates earlier than NRMP, so applicants using it must prepare their application materials sooner. |
| Who runs ERAS, and which programs does it cover? | The AAMC administers ERAS, which, according to the same match system guide, lets applicants apply to ACGME-accredited residency programs. |
| Does starting medicine later point toward a particular specialty? | A peer-reviewed analysis found a positive correlation between older age at admission to medical school and selecting family medicine. It is a pattern across trainees, not a rule for any individual couple. |
| How long is a combined family and emergency medicine path? | The same analysis discusses a proposed total of 4 years of training for such a combined path, and describes that proposal as offering little incentive. |